

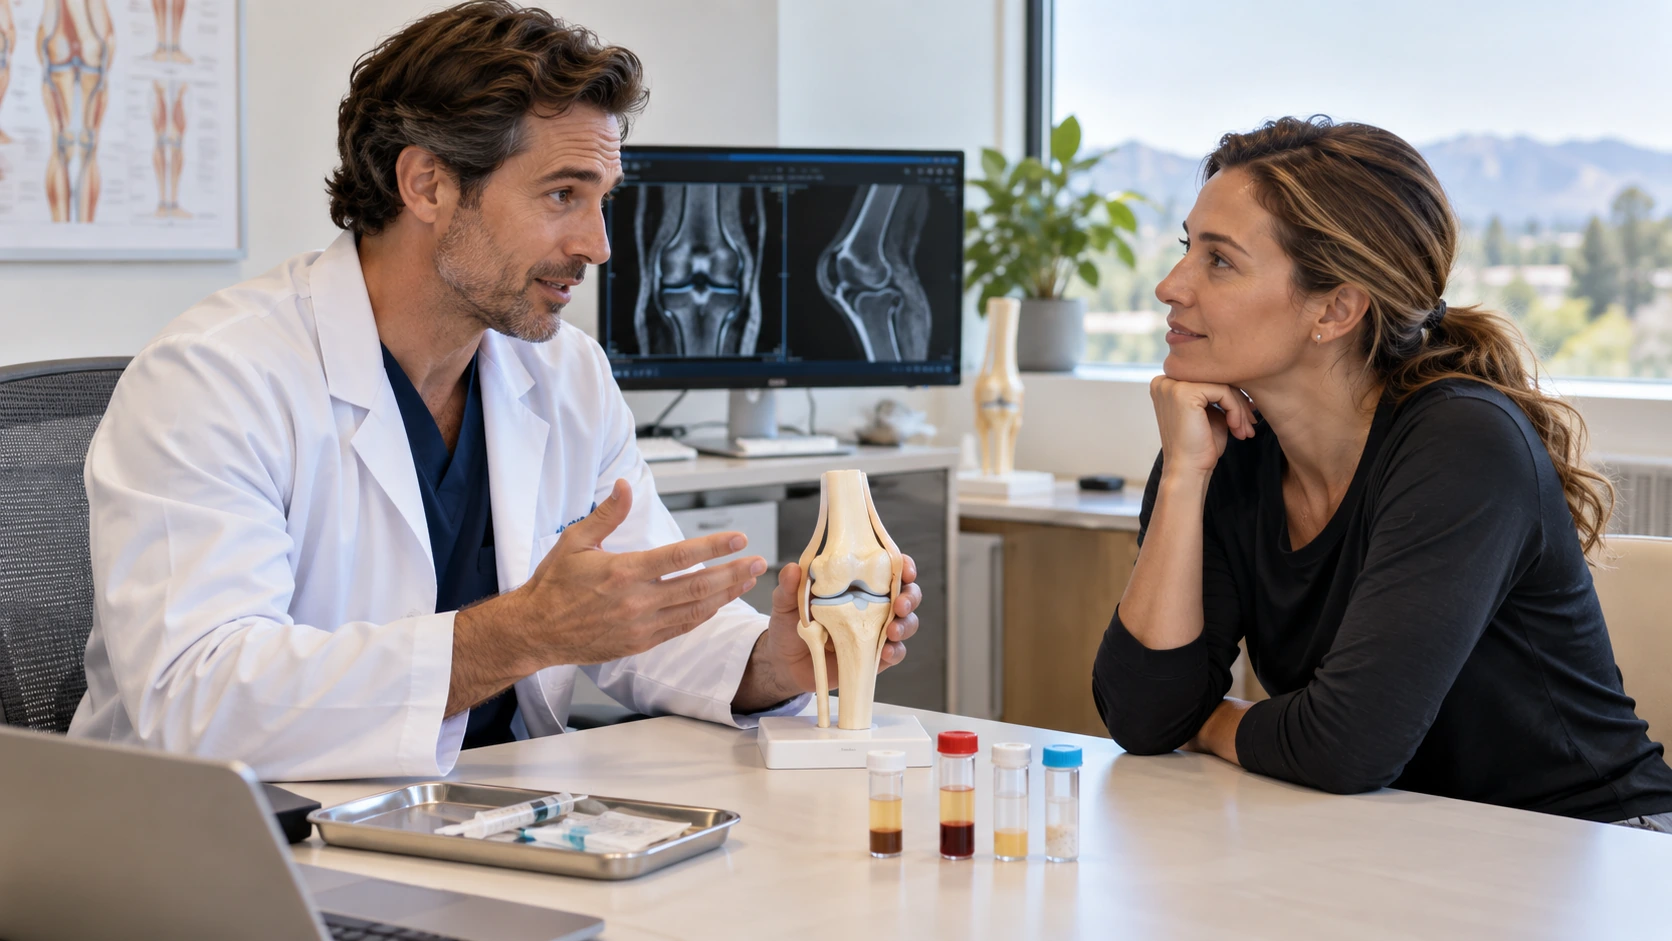
If you are exploring injection options for knee or other joint pain, you may have seen PRP, BMAC, and “stem cell” injections presented as similar treatments. They are not the same. They use different materials, involve different procedures, and have different levels of research and regulatory status.
There is no single option that is best for everyone. The right discussion starts with an accurate diagnosis, your goals, the severity of the joint problem, and a physician’s review of the evidence and alternatives. These injections should not be described as proven ways to regrow cartilage, cure arthritis, or avoid surgery. For a broader overview, read about regenerative orthopedic medicine and the distinction between orthobiologics and regenerative medicine.
Quick Comparison: PRP, BMAC, and “Stem Cell” Injections
| Option | What is injected? | Where it comes from | What to know |
|---|---|---|---|
| PRP | A preparation of the patient’s own blood with a higher concentration of platelets | Blood draw, processed before injection | Formulations and protocols vary. Research for knee osteoarthritis is mixed, and results are not guaranteed. |
| BMAC | Concentrated bone marrow aspirate, containing a mixture of cells and signaling components | Bone marrow aspirated from the patient, commonly from the pelvis, then concentrated | Requires a marrow harvest procedure. It is not a purified stem-cell dose. Direct comparison research is limited. |
| Products marketed as “stem cell” injections | The term may refer to very different products, including donor-derived tissue products, cell preparations, or other biologics | May be autologous (from the patient) or allogeneic (from a donor); the source and processing vary | Ask exactly what the product is. FDA says regenerative medicine products have not been approved to treat orthopedic conditions such as osteoarthritis or knee pain. |
The comparison above is general education. Product composition, preparation, treatment protocol, and regulations matter. Ask a qualified orthopedic physician to explain the specific product being offered.
What Is PRP?
Platelet-rich plasma, or PRP, is made from a sample of your blood. A processing system separates and concentrates platelets in plasma, which is then injected into a targeted area. Platelets release signaling proteins involved in the body’s normal response to injury, but the presence of these signals does not establish that an injection repairs cartilage or reverses arthritis.
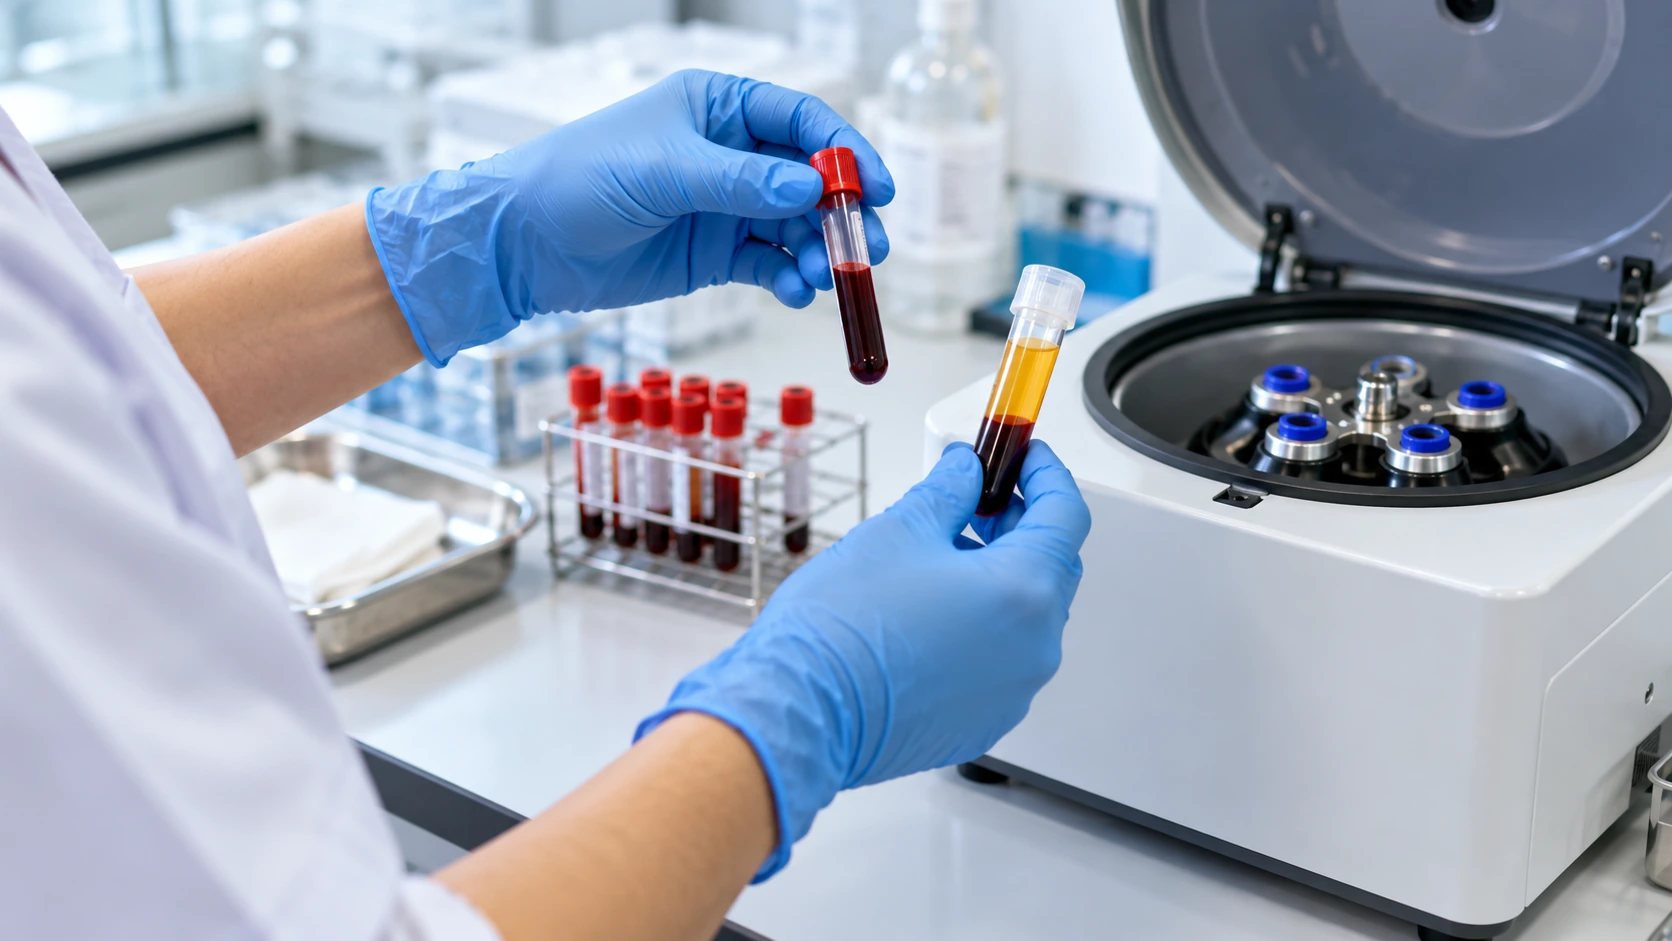
PRP is not one standardized formula. Preparation can vary in platelet concentration, white blood cell content, activation method, and the number and timing of injections. That variation makes it difficult to compare results across studies and clinics. Ask the physician what preparation they use, why they chose it for your condition, and what outcomes the supporting research actually measured. The clinic’s PRP, BMAC, and orthobiologics overview gives more context about how these treatment categories differ.
What Is BMAC?
Bone marrow aspirate concentrate, or BMAC, is prepared from a sample of the patient’s bone marrow. A physician draws marrow—often from the pelvic bone—and processes it to concentrate components of the aspirate. The final preparation is a mixture; it should not be presented as a purified, uniform “stem cell” product or as a known dose of stem cells.

Because BMAC requires a marrow aspiration in addition to the injection, the procedure is more involved than a blood draw for PRP. Patients should discuss expected discomfort, potential complications, recovery, cost, and why BMAC is being considered for their diagnosis. See the clinic’s BMAC therapy guide for more on the procedure and evaluation process.
What Does “Stem Cell Injection” Mean?
“Stem cell injection” is a broad marketing phrase, not a precise description of one standardized treatment. It may refer to a patient’s own bone-marrow or fat-derived preparation, a donor-derived tissue product, or another product advertised as regenerative. These are not interchangeable. Some products promoted as stem cell treatments may not contain the cells patients assume they do.
Ask the clinic to identify the source of the material, how it is processed, whether it contains living cells, what regulatory authorization applies, and which published clinical trial studied that exact product for your condition. This guide to autologous and donor-derived stem cell products explains why product source matters. FDA registration of a clinic or listing of a product is not the same as FDA approval to treat a joint condition.
What Does the Evidence Say About PRP vs. BMAC?
Research does not establish one injection as the best choice for every patient. A prospective randomized trial enrolled 90 adults with symptomatic knee osteoarthritis and compared BMAC with PRP. At two years, the researchers reported equivalent outcomes between the two groups. That is useful direct evidence, but it is one study in people with mild-to-moderate knee osteoarthritis; it does not establish that either treatment works for every joint, diagnosis, or patient.

A 2024 network meta-analysis of 48 studies (9,338 knees) reported that PRP, BMAC, and hyaluronic acid ranked among injections with a higher likelihood of improvement in pain and function at six months or longer. However, BMAC accounted for only 2.5% of the included treatment arms, compared with 21.5% for PRP. The authors concluded PRP improved pain and function compared with placebo at the minimum six-month follow-up. Ranking results should not be interpreted as proof that one treatment is superior for an individual, nor do they demonstrate cartilage regrowth.
Studies differ in who they enroll, how they prepare the injections, the number of treatments, and how they measure improvement. A reasonable conversation includes what is known, what remains uncertain, and what standard treatment options may also fit your situation. The clinic’s patient guide to regenerative medicine, PRP, and orthobiologics offers additional background on these terms.
FDA Status: What Patients Should Know
In the United States, the FDA states that regenerative medicine therapies have not been approved to treat orthopedic conditions such as osteoarthritis, tendonitis, or knee pain. The FDA also cautions patients about products marketed as stem cells, exosomes, and certain tissue-derived products. A clinic should not imply that an unapproved product is FDA-approved for joint pain or that registration alone proves effectiveness or approval.
PRP and BMAC are autologous preparations made from a patient’s own blood or marrow and are distinct from donor-derived stem-cell or exosome products. Their regulatory treatment can depend on how they are manufactured, processed, and used. Do not assume every product described as “regenerative” has the same FDA status. Ask the physician to explain the exact product and the basis for any regulatory claim.
Potential Benefits, Risks, and Practical Considerations
Some patients report less pain or improved function after an injection, but individual response varies and benefits are not guaranteed. The procedure can also cause temporary soreness, swelling, bleeding, or infection; a marrow harvest adds a separate procedural site and associated discomfort. The exact risks depend on the preparation and injection site, so review them with the treating physician.
If you are comparing costs, the clinic also provides information about treatment financing. Before deciding, discuss:
- The diagnosis and whether imaging or other evaluation is needed.
- What material will be used and where it comes from.
- The evidence for that exact preparation and condition.
- Possible side effects, recovery time, and how success will be measured.
- Total cost, insurance coverage, and what happens if symptoms continue.
- Established nonsurgical and surgical options, including their likely benefits and risks.
How Do the Procedures Differ?
PRP usually begins with a blood draw. The sample is processed in a centrifuge or preparation system, and the resulting plasma is injected into the selected area. Some protocols use one injection, while others involve a series. The plan depends on the clinician’s protocol and the condition being treated, so ask how many visits are proposed and what the evidence says about that schedule.
BMAC involves collecting marrow, commonly from the pelvic bone, and processing it before injection. This means there is both a harvest site and an injection site to consider. Ask how the marrow is collected, what type of anesthesia or numbing is used, what soreness to expect, and what restrictions apply after the procedure. A clinic should be able to explain the steps in plain language before you agree to treatment.
The phrase “stem cell injection” does not tell you how a procedure is performed. One clinic may be describing an autologous marrow preparation; another may offer a donor-derived tissue product. Ask for the exact product name, source, preparation method, and written information about the procedure. If those details are not clear, it is difficult to compare the offer with published research or understand its regulatory status.
How to Evaluate Treatment Claims
Promotional language can make an injection sound more certain than the research supports. Look for clear answers to practical questions instead of relying on broad phrases such as “regenerative,” “natural,” or “stem cell.” Those terms alone do not tell you what is in the injection or how likely it is to help with your diagnosis.
When reviewing a study or a clinic’s explanation, check whether the research involved the same condition and joint, a similar preparation, and a comparable dose and schedule. A study of one PRP formulation, for example, does not automatically prove that every PRP preparation will produce the same result. Likewise, evidence about symptoms after injection cannot establish that cartilage has regrown unless the study measured and demonstrated that outcome.
Ask how the clinic defines improvement. It may track pain scores, walking distance, daily activities, or use of other treatments. Knowing the planned follow-up schedule and what happens if symptoms do not improve can help set realistic expectations. Be cautious if an offer relies mainly on testimonials, guarantees a particular result, or says that an injection will definitely prevent a joint replacement.
What Other Joint-Pain Care Can Be Discussed?
An injection is one possible part of a larger care plan. Depending on the diagnosis, a clinician may discuss activity changes, physical therapy or exercise, weight management where relevant, medicines, other types of injections, bracing, or surgical evaluation. These options are not interchangeable, and what is appropriate depends on your health, symptoms, examination, imaging when needed, and treatment goals.
Ask the physician to compare the proposed injection with reasonable alternatives for your specific situation. That comparison should include potential benefits, limitations, risks, cost, recovery time, and whether delaying another treatment could matter. You can review the clinic’s non-surgical regenerative medicine overview and orthopedic treatment options as you prepare questions. A second opinion may help if you are uncertain about an expensive procedure or have been told that only one option is available.
What to Expect After an Evaluation
A treatment evaluation should begin with the problem you are trying to solve. Bring a list of symptoms, when they occur, what makes them better or worse, prior treatments, relevant imaging or records, medications, and questions about work, exercise, or daily activities. The clinician can then assess whether the pain is likely coming from the joint or another structure and whether further evaluation is appropriate.
If an injection is discussed, ask what outcome would count as meaningful improvement for you and when it would be assessed. Ask whether temporary post-procedure soreness is expected, which activities you should avoid and for how long, and whom to contact if you have a concern. Follow the treating clinician’s instructions for your individual case; recovery guidance may differ by injection type and treatment site.
An evaluation does not obligate you to proceed. You can take time to review written information, verify the product and its regulatory claims, and weigh the proposed treatment against other choices. A responsible discussion should make space for questions and should not depend on pressure to decide immediately.
Which Option May Be Appropriate for Joint Pain?
There is no universal answer to “Which is better: PRP, BMAC, or a stem cell injection?” The options differ in source material and procedure, and the evidence does not support a blanket promise that one will heal a joint or prevent surgery. The choice depends on the specific diagnosis, prior care, overall health, preferences, and the quality and applicability of the evidence. For knee symptoms in particular, review the information on knee arthritis evaluation and treatment and this article on whether stem cell therapy can help knee arthritis.
A physician evaluation can help determine whether an injection is reasonable to discuss and how it fits with other care options. For more detail, read about BMAC therapy in Dallas and orthopedic treatment options. To discuss your symptoms and questions with the clinic, contact the team to schedule a treatment evaluation.
Frequently Asked Questions
Is PRP the same as a stem cell injection?
No. PRP is prepared from a patient’s blood and concentrates platelets. “Stem cell injection” can mean different products and sources, so ask for the exact composition and source rather than relying on the label.
Does BMAC contain stem cells?
BMAC is a concentrated mixture from bone marrow, not a purified or standardized stem-cell product. The amount and type of cells can vary. A clinic should explain what is known about its preparation and avoid promising a specific cell dose or outcome without evidence.
Can PRP or BMAC regrow cartilage?
Current evidence does not justify promising that either injection regrows cartilage or reverses osteoarthritis. Research findings about pain or function are not the same as proof of cartilage regeneration.
Are donor stem-cell or exosome injections FDA-approved for knee arthritis?
The FDA states that regenerative medicine products have not been approved to treat orthopedic conditions such as osteoarthritis or knee pain. Ask a physician to identify the exact product and explain its regulatory status.
How should I compare clinics offering these injections?
Ask what exact material is used, whether it comes from you or a donor, how it is processed, what research supports that specific use, what risks and costs apply, and how outcomes are tracked. Be cautious of guarantees, claims of a cure, promises to regrow cartilage, or claims that treatment will definitely help you avoid surgery.
Medical review note: Have a licensed orthopedic physician review the medical claims, product descriptions, procedure risks, regulatory language, and treatment CTA before publication. This article is educational and is not a diagnosis or individualized treatment advice.